(talazoparib)
14 CLINICAL STUDIES
14 CLINICAL STUDIES
14.1 Deleterious or Suspected Deleterious Germline BRCA-mutated HER2-negative Locally Advanced or Metastatic Breast Cancer
EMBRACA (NCT01945775) was an open-label study in which patients (N=431) with gBRCAm HER2-negative locally advanced or metastatic breast cancer were randomized 2:1 to receive TALZENNA 1 mg or healthcare provider's choice of chemotherapy (capecitabine, eribulin, gemcitabine, or vinorelbine) until disease progression or unacceptable toxicity. Randomization was stratified by prior lines of chemotherapy for metastatic disease (0 vs 1, 2, or 3), by triple-negative disease status [triple-negative breast cancer (TNBC) vs non-TNBC], and history of central nervous system (CNS) metastasis (yes vs no).
Patients received no more than 3 prior cytotoxic chemotherapy regimens for their metastatic or locally advanced disease. Patients were required to have received treatment with an anthracycline and/or a taxane (unless contraindicated) in the neoadjuvant, adjuvant, and/or metastatic treatment setting. First-line treatment for advanced or metastatic disease with no prior adjuvant chemotherapy was allowed if the investigator determined that 1 of the 4 chemotherapy choices in the control arm would be an appropriate treatment option for the patient. Patients with prior platinum therapy for advanced disease were required to have no evidence of disease progression during platinum therapy. No prior treatment with a PARP inhibitor was permitted. Of the 431 patients randomized in the EMBRACA study, 408 (95%) were centrally confirmed to have a deleterious or suspected deleterious gBRCAm using a clinical trial assay; out of which 354 (82%) were confirmed using the BRACAnalysis CDx®. BRCA mutation status [breast cancer susceptibility gene 1 (BRCA1)-positive or breast cancer susceptibility gene 2 (BRCA2)-positive] was similar across both treatment arms.
The median age of patients treated with TALZENNA was 46 years (range: 28 to 84) and 51 years (range: 24 to 89) among patients treated with chemotherapy. Among all randomized patients, 1% vs 2% were males, 67% vs 75% were White; 11% vs 11% were Asian, and 4% vs 1% were Black or African American in the TALZENNA and chemotherapy arms, respectively. Almost all patients (98%) in both arms had an Eastern Cooperative Oncology Group (ECOG) performance status of 0 or 1. Approximately 56% of patients had estrogen receptor-positive and/or progesterone receptor-positive disease; 44% of patients had triple-negative disease, and the proportions were balanced across both treatment arms. Fifteen percent (15%) of patients in the TALZENNA arm and 14% of patients in the chemotherapy arm had a history of CNS metastases. Ninety-one percent (91%) of patients in the TALZENNA arm had received prior taxane therapy, and 85% had received prior anthracycline therapy in any setting. Sixteen percent (16%) of patients in the TALZENNA arm and 21% of patients in the chemotherapy arm had received prior platinum treatment in any setting. The median number of prior cytotoxic regimens for patients with advanced breast cancer was one; 38% received no prior cytotoxic regimens for advanced or metastatic disease, 37% received one, 20% received two, and 5% received three or more prior cytotoxic regimens.
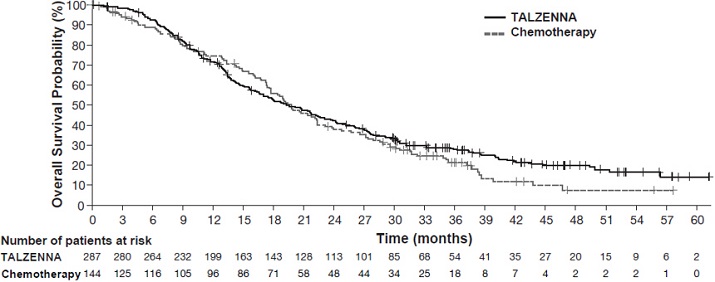
The major efficacy outcome measure was progression-free survival (PFS) evaluated according to Response Evaluation Criteria in Solid Tumors (RECIST) version 1.1, as assessed by blinded independent central review (BICR). A statistically significant improvement in PFS was demonstrated for TALZENNA compared to chemotherapy. A sensitivity analysis of investigator-assessed PFS was consistent with the BICR-assessed PFS results. Consistent PFS results were observed across patient subgroups defined by study stratification factors (prior lines of chemotherapy, TNBC status, and history of CNS metastases). Efficacy data from the EMBRACA study are summarized in Table 11, and the Kaplan-Meier curves for PFS are shown in Figure 1 and final overall survival (OS) in Figure 2.
| Abbreviations: BICR=blinded independent central review; CI=confidence interval; DOR=duration of response; ITT=intent-to-treat; N=number of patients; ORR=objective response rate; OS=overall survival; PFS=progression-free survival. | ||
| ||
TALZENNA | Chemotherapy | |
PFS by BICR | N=287 | N=144 |
Disease progression or deaths, n (%) | 186 (65) | 83 (58) |
Median months (95% CI) | 8.6 (7.2, 9.3) | 5.6 (4.2, 6.7) |
Hazard ratio (95% CI)* | 0.54 (0.41, 0.71) | |
p-value† | p<0.0001 | |
Patients with Measurable Disease by Investigator‡ | N=219 | N=114 |
ORR, % (95% CI)§ | 50.2 (43.4, 57.0) | 18.4 (11.8, 26.8) |
Median¶ DOR months (95% CI) | 6.4 (5.4, 9.5) | 3.9 (3.0, 7.6) |
OS | N=287 | N=144 |
Deaths, n (%) | 216 (75) | 108 (75) |
Median months (95% CI) | 19.3 (16.6, 22.5) | 19.5 (17.4, 22.4) |
Hazard ratio (95% CI)* | 0.85 (0.67, 1.07) | |
p-value† | p=0.1693 | |
Figure 1. Kaplan-Meier Curves of PFS – EMBRACA Study
| Abbreviation: PFS=progression-free survival. |
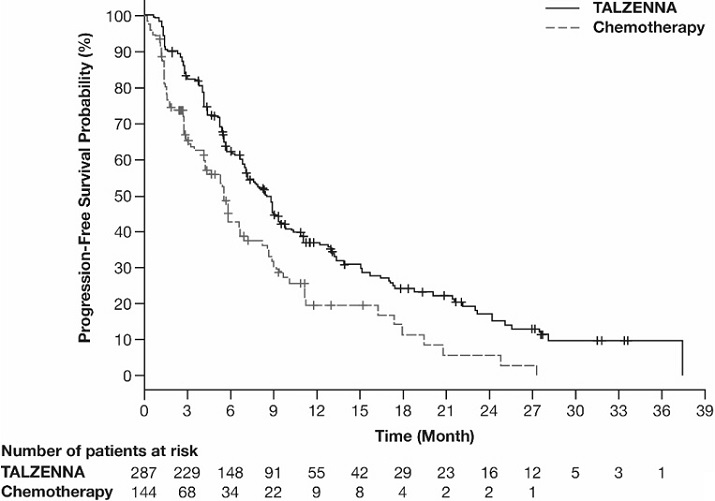 |
Figure 2. Kaplan-Meier Curves of OS – EMBRACA Study (ITT Population)
| Abbreviations: ITT=intent-to-treat; OS=overall survival. |
 |
14.2 HRR Gene-Mutated Prostate Cancer
mAPMR Prostate Cancer
TALAPRO-2
The efficacy of TALZENNA with enzalutamide was evaluated in TALAPRO-2 (NCT03395197), a randomized, double-blind, placebo-controlled, multi-cohort trial in which 399 patients with HRR gene-mutated (HRRm) mAPMR prostate cancer were randomized 1:1 to receive enzalutamide 160 mg daily plus either TALZENNA 0.5 mg or placebo daily until unacceptable toxicity or disease progression. Mutation status of HRR genes was determined prospectively using solid tumor tissue or circulating tumor DNA (ctDNA)-based next generation sequencing tests. Patients were required to have a mutation in at least one of 12 genes involved directly or indirectly in the HRR pathway (ATM, ATR, BRCA1, BRCA2, CDK12, CHEK2, FANCA, MLH1, MRE11A, NBN, PALB2, or RAD51C). All patients received a GnRH analog or had had a prior bilateral orchiectomy and needed to have progressed on prior androgen deprivation therapy. Prior treatment with a CYP17 inhibitor or docetaxel for mAPMN/S prostate cancer was permitted. Randomization was stratified by previous treatment with a CYP17 inhibitor or docetaxel (yes/no).
The median age was 70 years (range: 41 to 90); 100% were male; 68% were White, 21% Asian, 2.8% Black, 0.8% Other, 7% unknown/not reported; 12% were Hispanic/Latino; and baseline ECOG performance status was 0 (62%) or 1 (38%). Thirty-nine percent of patients had bone-only disease; 15% had visceral disease. In the mAPMN/S prostate cancer setting, 29% of patients had received docetaxel and 9% had received a prior CYP17 inhibitor. The most commonly mutated HRR genes (>5%), including co-occurring mutations, were: BRCA2 (34%), ATM (22%), CDK12 (19%), CHEK2 (18%), and BRCA1 (6%).
The major efficacy outcome measure was radiographic progression-free survival (rPFS) evaluated according to RECIST, version 1.1 and Prostate Cancer Working Group (PCWG3) (bone) criteria, assessed by blinded independent central review (BICR). An additional efficacy outcome measure was overall survival (OS).
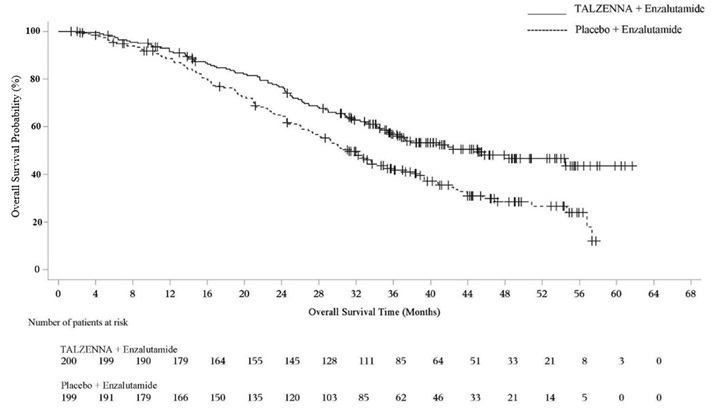
Statistically significant improvements in rPFS and OS were demonstrated in patients randomized to TALZENNA with enzalutamide compared with placebo with enzalutamide. Efficacy results are presented in Table 12, and Figures 3 and 4.
| Abbreviations: CI=confidence interval; NR=not reached. | |||
TALZENNA with Enzalutamide N=200 | Placebo with Enzalutamide N=199 | ||
Radiographic Progression-Free Survival by BICR | |||
Number of events, n (%) | 66 (33) | 104 (52) | |
Median months (95% CI) | NR (21.9, NR) | 13.8 (11.0, 16.7) | |
Hazard ratio (95% CI)* | 0.45 (0.33, 0.61) | ||
p-value† | p<0.0001 | ||
| |||
Overall Survival | |||
Deaths, n (%) | 93 (47) | 126 (63) | |
Median months (95% CI) | 45.1 (35.4, NR) | 31.1 (27.3, 35.4) | |
Hazard ratio (95% CI)* | 0.62 (0.48, 0.81) | ||
p-value† | p=0.0005 | ||
Figure 3. Kaplan-Meier Curves of rPFS - TALAPRO-2 (HRRm mAPMR Prostate Cancer)
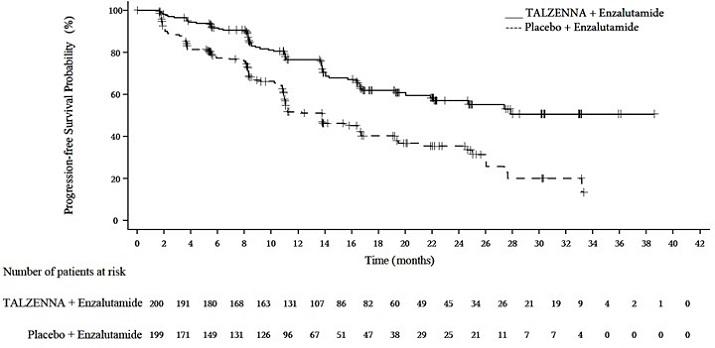 |
Figure 4. Kaplan-Meier Curves of OS – TALAPRO-2 (HRRm mAPMR Prostate Cancer)
Exploratory subgroup analyses of rPFS and OS for patients with BRCA-mutated (BRCAm) and non-BRCAm HRRm are presented in Table 13.
| Abbreviations: CI=confidence interval; NR=not reached. | ||||
BRCAm | Non-BRCAm HRRm* | |||
TALZENNA with Enzalutamide N=71 | Placebo with Enzalutamide N=84 | TALZENNA with Enzalutamide N=129 | Placebo with Enzalutamide N=115 | |
Radiographic Progression-Free Survival | ||||
Number of events, n (%) | 15 (21) | 54 (64) | 51 (40) | 50 (43) |
Median months (95% CI) | NR (NR, NR) | 11.0 (8.3, 11.1) | 24.7 (16.4, NR) | 16.7 (13.8, 27.7) |
Hazard ratio (95% CI) | 0.20 (0.11, 0.36) | 0.74 (0.50, 1.09) | ||
| ||||
Overall Survival | ||||
Deaths, n (%) | 30 (42) | 56 (67) | 63 (49) | 70 (61) |
Median months (95% CI) | NR (35.4, NR) | 28.5 (24.5, 34.4) | 42.4 (34.2, NR) | 32.6 (28.0, 42.2) |
Hazard ratio (95% CI)† | 0.48 (0.31, 0.75) | 0.71 (0.51, 1.00) | ||
mAPMN/S Prostate Cancer
TALAPRO-3
The efficacy of TALZENNA in combination with enzalutamide was evaluated in TALAPRO-3 (NCT04821622), a randomized, double-blind, placebo-controlled, trial in which 599 patients with HRRm mAPMN/S prostate cancer were randomized 1:1 to receive enzalutamide 160 mg daily plus either TALZENNA 0.5 mg or placebo daily until unacceptable toxicity or disease progression. Mutation status of HRR genes was determined prospectively using solid tumor tissue or ctDNA-based next generation sequencing tests. Patients were required to have a mutation in at least one of 12 genes involved directly or indirectly in the HRR pathway (ATM, ATR, BRCA1, BRCA2, CDK12, CHEK2, FANCA, MLH1, MRE11A, NBN, PALB2, or RAD51C). All patients received a GnRH analog, or had a prior bilateral orchiectomy. Patients must have initiated androgen deprivation therapy or undergone a bilateral orchiectomy in the mAPMN/S prostate cancer setting up to 3 months prior to randomization with or without an androgen receptor pathway inhibitor (ARPI) but were not allowed to have received prior docetaxel. Randomization was stratified by de novo mAPMN/S vs relapsed mAPMN/S prostate cancer, high vs low volume disease, and BRCA vs non-BRCA mutational status.
The median age was 70 years (range: 44 to 89); 100% were male; 57% were White, 39% Asian, 2% Black, 1% Other, 2% unknown/not reported; 10% were Hispanic/Latino, 87% were Not Hispanic or Latino, 3% unknown/not reported; and baseline ECOG performance status was 0 (68%) or 1 (32%). Thirteen percent of patients had received a prior ARPI in the mAPMN/S setting. There were 398 (66%) and 438 (73%) patients with high volume disease and de novo mAPMN/S prostate cancer, respectively, and 307 (51%) with both de novo and high-volume disease. The most commonly mutated HRR genes (>5%), including co-occurring mutations, were: BRCA2 (30%), ATM (28%), CDK12 (19%), CHEK2 (15%) and ATR (7%).
The major efficacy outcome measure was rPFS evaluated according to RECIST, version 1.1 and PCWG3 (bone) criteria, assessed by investigator. An additional efficacy outcome measure was OS.
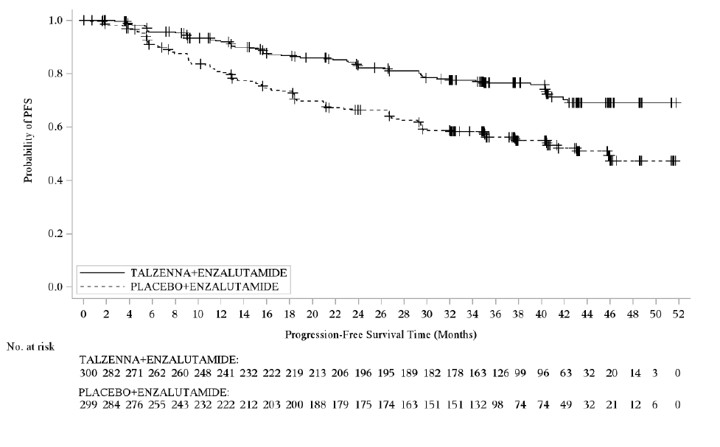
A statistically significant improvement in rPFS was demonstrated in patients randomized to TALZENNA with enzalutamide compared with those randomized to placebo with enzalutamide. At the time of the rPFS analysis, OS data were immature with 28% deaths in the overall population. Efficacy results are presented in Table 14 and Figure 5.
| Abbreviations: CI=confidence interval; NR=not reached. | ||
| ||
TALZENNA with Enzalutamide N=300 | Placebo with Enzalutamide N=299 | |
Radiographic Progression-Free Survival by Investigator | ||
Number of events, n (%) | 67 (22) | 126 (42) |
Median months (95% CI) | NR (NR, NR) | 45.8 (37.7, NR) |
Hazard ratio (95% CI)* | 0.48 (0.36, 0.65) | |
p-value† | p<0.0001 | |
Figure 5. Kaplan-Meier Curves of rPFS - TALAPRO-3 (HRRm mAPMN/S Prostate Cancer)
 |
Exploratory subgroup analyses of rPFS for patients with BRCAm and non-BRCAm HRRm are presented in Table 15.
| BRCAm | Non-BRCAm HRRm | |||
|---|---|---|---|---|
| TALZENNA with Enzalutamide N=104 | Placebo with Enzalutamide N=103 | TALZENNA with Enzalutamide N=196 | Placebo with Enzalutamide N=196 | |
| Abbreviations: CI=confidence interval; IRT=interactive response technology; NR=not reached. | ||||
Radiographic Progression-Free Survival by Investigator | ||||
Number of events, n (%) | 22 (21) | 49 (48) | 45 (23) | 77 (39) |
Median months (95% CI) | NR (NR, NR) | 35.1 (18.6, NR) | NR (NR, NR) | NR (40.5, NR) |
Hazard ratio (95% CI)† | 0.37 (0.22, 0.61) | 0.57 (0.39, 0.82) | ||
MEDICATION GUIDE
| This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: 10/2026 | |
PATIENT INFORMATION | |
What is the most important information I should know about TALZENNA?
| |
○ weakness ○ weight loss ○ fever ○ frequent infections | ○ blood in urine or stool ○ shortness of breath ○ feeling very tired ○ bruising or bleeding more easily |
○ every month during treatment with TALZENNA. ○ weekly if you have low blood cell counts that last a long time. Your healthcare provider may change your dose, temporarily stop, or permanently stop treatment with TALZENNA if you get certain side effects. See “What are the possible side effects of TALZENNA?” below for other side effects of TALZENNA. | |
What is TALZENNA?
Your healthcare provider will perform a test to make sure that TALZENNA is right for you. It is not known if TALZENNA is safe and effective in children. | |
Before taking TALZENNA, tell your healthcare provider about all of your medical conditions, including if you:
Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. Taking TALZENNA with certain other medicines can affect how TALZENNA works and may cause side effects. | |
How should I take TALZENNA?
| |
What are the possible side effects of TALZENNA? TALZENNA may cause serious side effects, including: The most common side effects of TALZENNA when taken alone include: | |
|
|
The most common side effects of TALZENNA when taken in combination with enzalutamide include: | |
|
|
TALZENNA may cause fertility problems in males. This may affect your ability to father a child. Talk to your healthcare provider if this is a concern for you. | |
How should I store TALZENNA?
Keep TALZENNA and all medicines out of the reach of children. | |
General information about the safe and effective use of TALZENNA. | |
What are the ingredients in TALZENNA? 
| |
Additional Resources
Chat online with Pfizer Medical Information regarding your inquiry on a Pfizer medicine or vaccine.
Speak with a Pfizer Medical Information Professional regarding your Pfizer medicine or vaccine inquiry.
Available 9AM-5PM ET Monday to Friday; excluding holidays.
Submit a medical question for a Pfizer medicine or a vaccine.
The submission will be reviewed during our standard business hours.
To report an adverse event related to a Pfizer product and you are not part of a clinical trial* for this medication, click the link below to submit your information:
Pfizer Safety Reporting Site
*If you are involved in a clinical trial for either product, adverse events should be reported to your coordinating study site.
If you cannot use the above website to report an adverse event related to a Pfizer medication, please call (800) 438-1985.
You may also contact the U.S. Food and Drug Administration (FDA) directly to report adverse events or product quality concerns either online at www.fda.gov/medwatch or by calling (800) 332-1088.